Overview
Why Is A Stroke Diagnostic So Important?
Stroke is the number one missed diagnosis causing harm with 17% of strokes missed rising to 42% for strokes with dizziness symptoms. [Reference JHU 2022 paper] Of the 800,000 stokes per year, 160,000 die and 250,000 have severe disabilities, making stroke the number 1 cause of disability.
Patients arriving at an ER with stroke symptoms get blood drawn and a CT scan to rule out hemorrhagic stroke from bleeding in the brain. CT scans are negative for bleeding 87% of the time leaving symptoms as the primary tool to diagnose ischemic strokes from a blood clot. This leaves doctors with a critical diagnostic gap: how can we very quickly distinguish patients who look like they are having a stroke from those who actually are having a stroke? Almost half of patients going to Emergency Departments with symptoms consistent with stroke, actually have another problem that looks like a stroke, but isn’t.
Unlike heart attack where there is a blood test that reduces missed events to under 2%, there is no blood test to help with missed strokes. It is not for lack of effort as a 2026 meta-analysis published in Nature Communications cited 863 published assay or assay combinations over 30 years attempting to provide a blood test for stroke with not a single one showing clinical utility.[reference Paper]
While MRI is able to see ischemic strokes, it takes too long, is hard to schedule making it impractical and today it is not a viable acute diagnostic for stroke. While NSE protein assays were included in the 863 assays, they too were not clinically viable. The use of the measurement of enzymatic activity is new and the FDA breakthrough designation is clear evidence of it being different.
TETmedical’s NSE-FAST is the first acute blood test using the enzymatic activity of NSE to measure the level of recent neuronal injury. FDA granting the NSE-FAST Breakthrough Technology Designation and issued patents combine to indicate the NSE-FAST is innovative.
TETmedical received FDA Breakthrough Technology Designation in June 2026 following submission of early data showing a 96% sensitivity for acute ischemic strokes that are missed by standard CT scans.
Acute Brain Injury IVD for Stroke
TETmedical has developed the NSE-FAST (Functional Activity Stroke Test), an In Vitro Diagnostic (IVD) for stroke to be used with standard plate readers. The test fits into standard clinical practice in the Emergency Department, with a potential high sensitivity and negative predictive value that would be highly useful with significant potential payer cost savings and reduced patient risk.
The NSE-FAST in-vitro diagnostic is in clinical studies and not yet approved by the FDA for human use.
Given the speed and specificity attainable with our diagnostic platform, TET is focused on quantitatively measuring the levels of active Neuro-Specific Enolase (NSE), a protein released by damaged neurons.
TETMedical’s Revolutionary Approach
Addressing this gap is so important that scientists and doctors have been trying for decades to identify “biomarkers,” molecules in the bloodstream that will reveal the presence of dying and damaged brain cells. Because it is found in large amounts in each neuron, the protein Neuron-specific Enolase (NSE) has been well-studied as a candidate biomarker. Unfortunately, the vast majority of these efforts tried to identify NSE by using antibodies. Antibody-based detection methods have a number of problems: they often suffer from low signal:noise ratios reducing their sensitivity, their results vary depending on the antibodies used, and they tend to take long-periods of time to perform.
Because of the speed and specificity attainable with the TET diagnostic platform, we quantitatively measure newly released NSE through its activity. Unlike antibodies, TETmedical’s NSE-FAST has intrinsic signal amplification at the earliest stage. In <2 minutes from the time that plasma is added to the wells, the TET reaction reveals the amount of recently-released active NSE. A pilot pre-clinical study in a stroke center showed a clear difference between patients who had a brain injury and those presenting with stroke mimics, all using a standard hospital-based plate reader.*
NSE-FAST Does Not Change Standard of Care Stroke Workflow
Today – patients presenting at the hospital with stroke symptom as seen in the diagram below, have a blood draw for standard blood tests than are assessed clinically based on their symptoms with an often used NIH stroke scale (NIHSS) as a quantifier for symptoms. A non-contrast CT scan is then run to identify bleeding associated with a hemorrhagic stroke. If the CT is negative (about 85% of the time) the neurologist and ER doctors must then decide if it is really a stroke from a blood clot (an ischemic stroke) or just a stroke mimic from something else. With no objected blood test for brain injury this is sometimes difficult.
Just as the diagnosis of heart attack has been revolutionized by the diagnostic assays for the biomarker High Sensitivity Troponin (current market over half a billion dollars/year), the TET NSE-FAST will revolutionize the detection of stroke. In the US today, more than 80% of patients with stroke symptoms have a negative CAT scan for hemorrhagic stroke (a bleed) and clinicians depend entirely on symptoms to make a diagnosis. Many common symptoms can be vague and unspecific to stroke. Without a biomarker to identify “real” brain injury, many patients are misdiagnosed and treated with clot busters (i.e. TPA), putting them at risk due to causing bleeds.
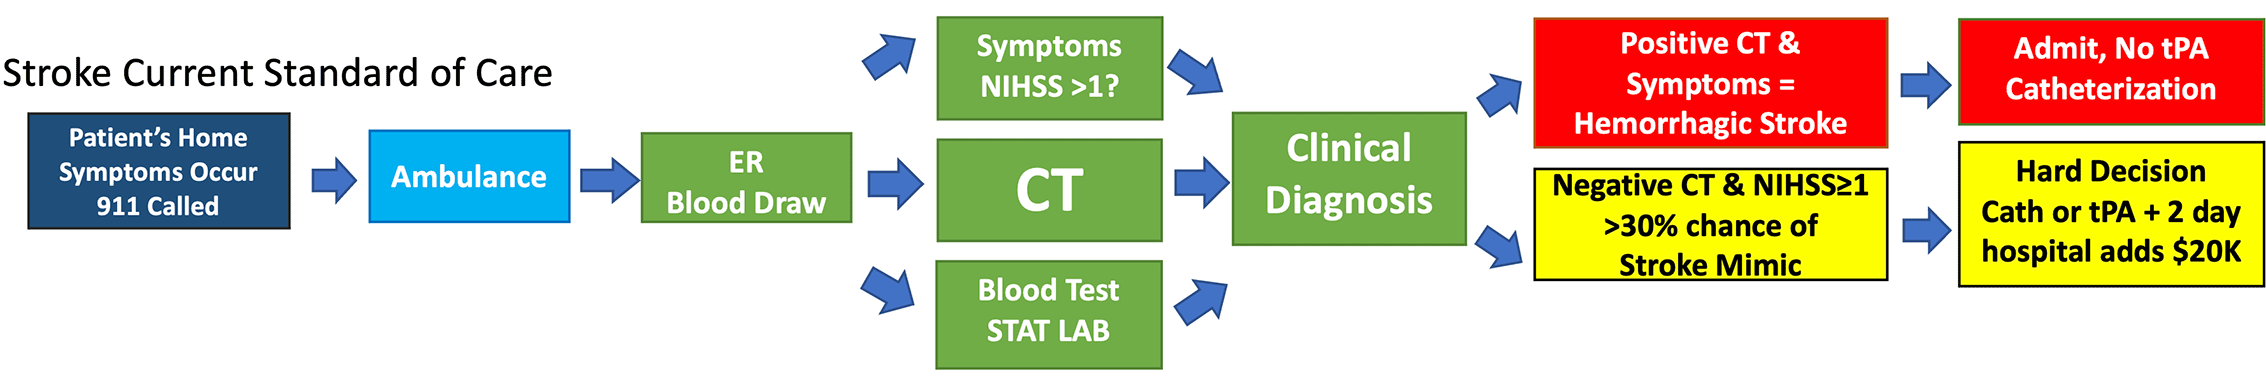
Just as the diagnosis of heart attack has been revolutionized by the diagnostic assays for the biomarker High Sensitivity Troponin (current market over half a billion dollars/year), the TET NSE-FAST will revolutionize the detection of stroke. In the US today, more than 80% of patients with stroke symptoms have a negative CAT scan for hemorrhagic stroke (a bleed) and clinicians depend entirely on symptoms to make a diagnosis. Many common symptoms can be vague and unspecific to stroke. Without a biomarker to identify “real” brain injury, many patients are misdiagnosed and treated with clot busters (i.e. TPA), putting them at risk due to causing bleeds.
About Enzymes
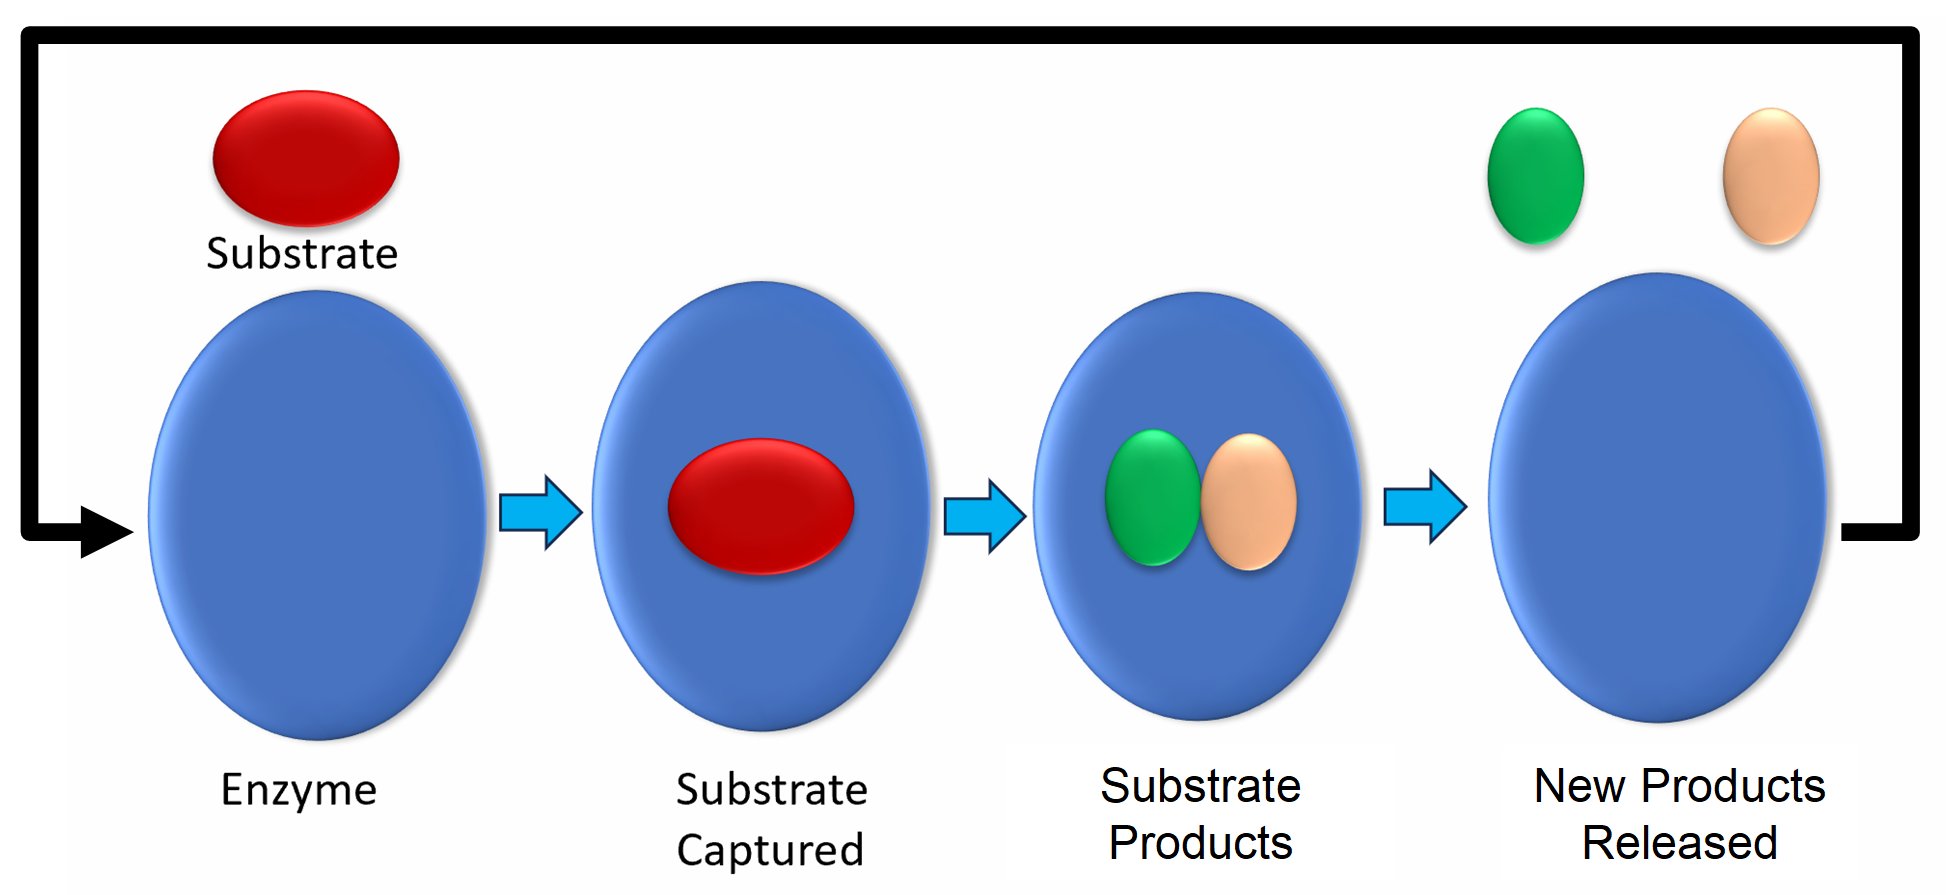
Enzymes are nature’s assembly line workers that as shown in the figure below, they attach to an organic compound or substrate, change it, release the result and do it again up to a thousand times a second.
How the NSE-FAST Works
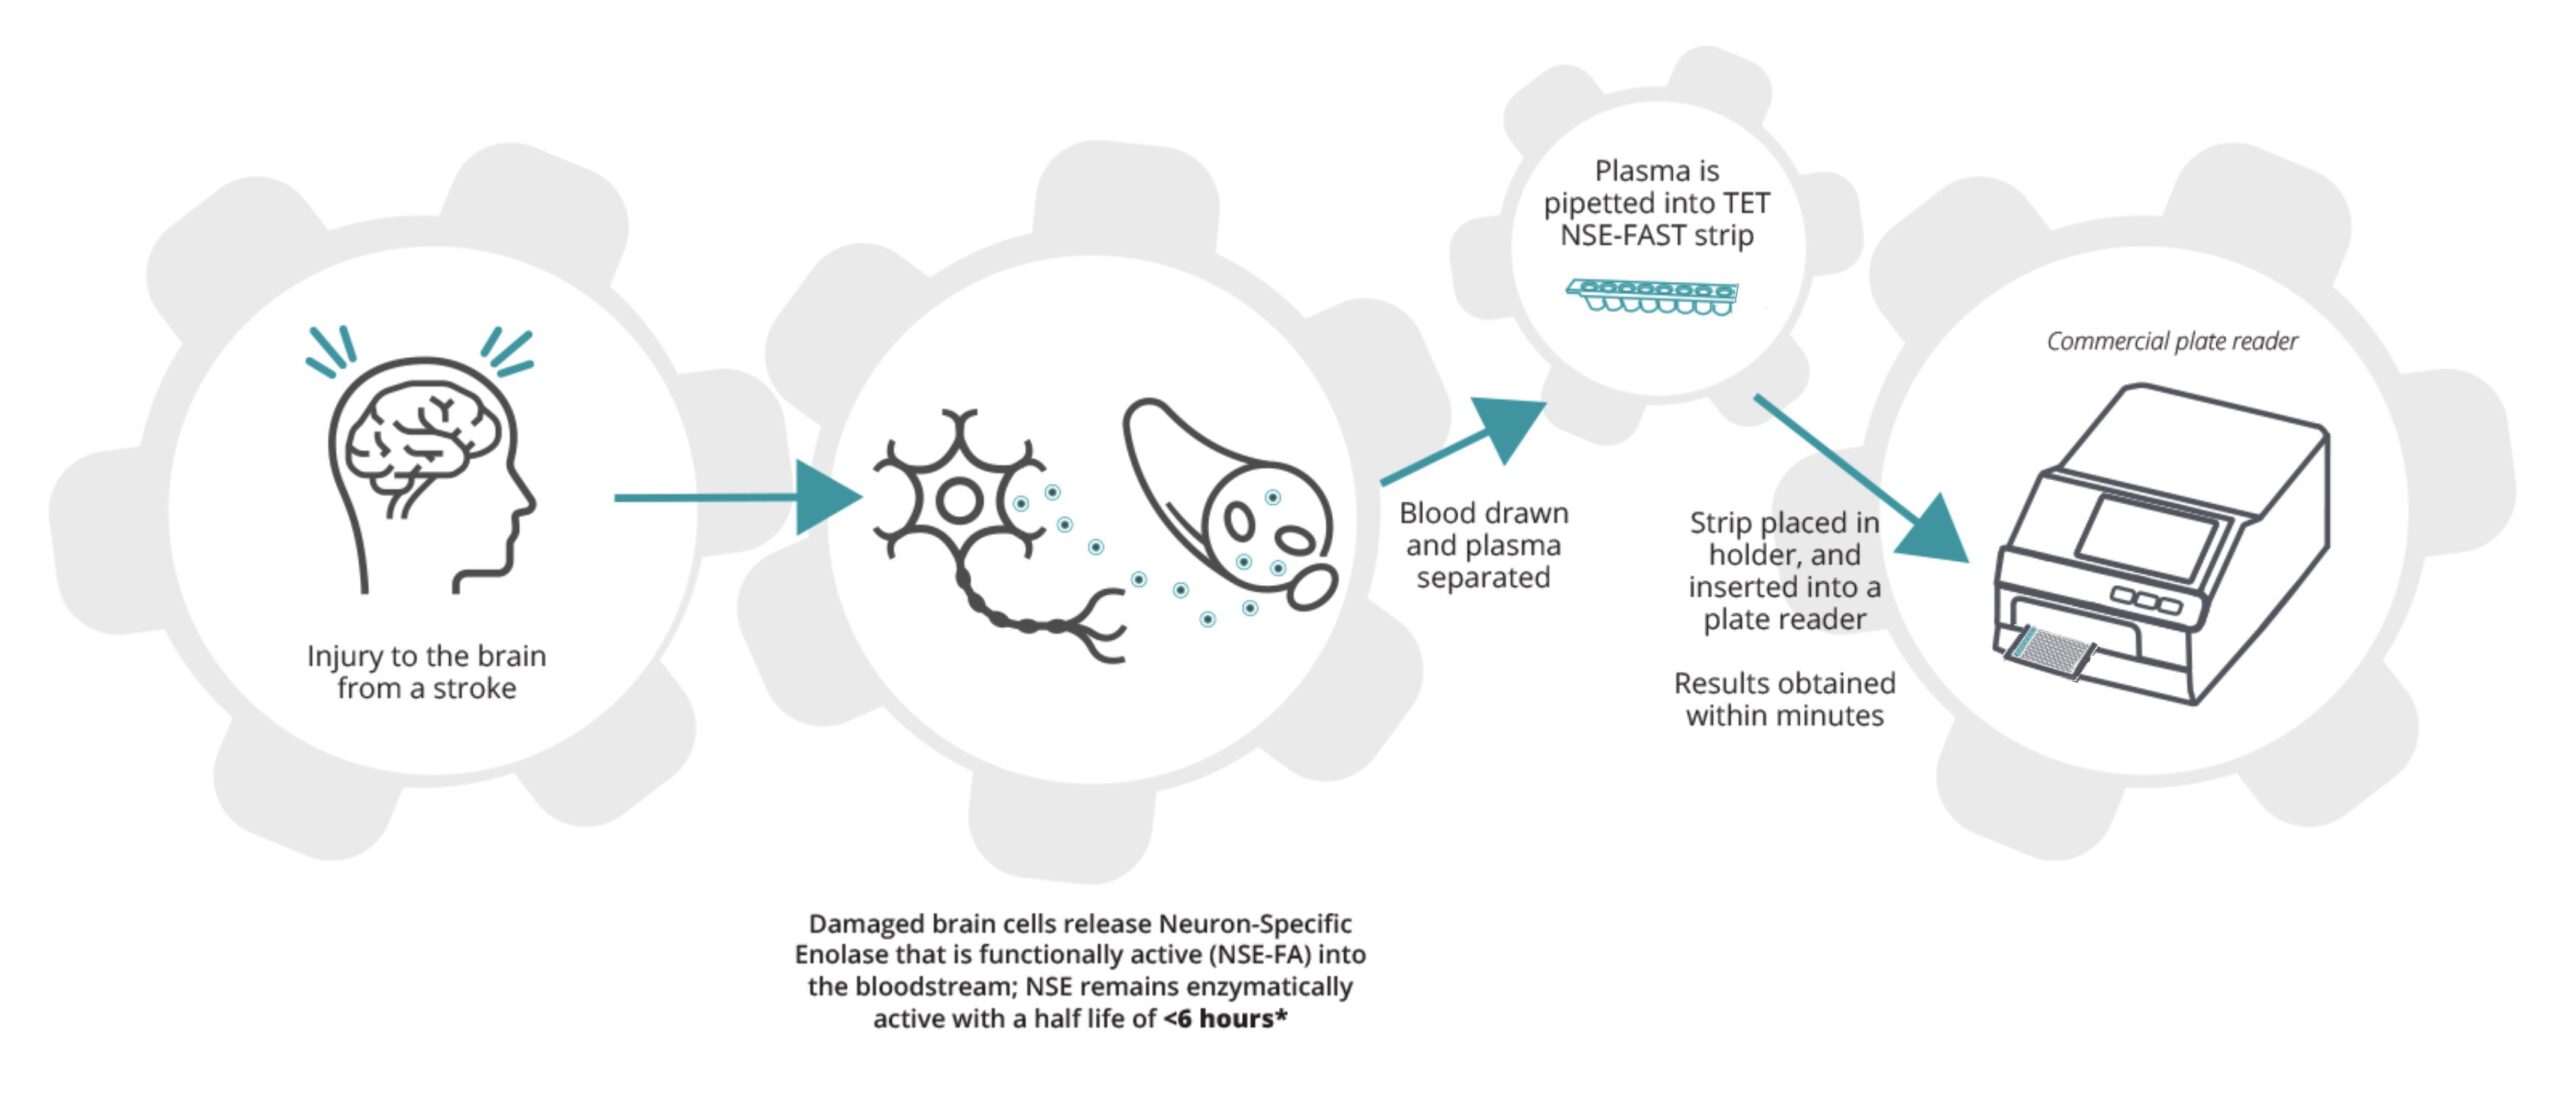
When there is injury to the brain from a stroke damaged neurons release cell contents into the bloodstream including the active enzyme NSE that makes up about 4% of the contents of a neuron. NSE remains active in the blood with a half life of <6 hours when it loses its activity but remains as a protein. Blood drawn and spun down to plasma. About 20 microliters of plasma is pipetted into each of the 12 wells in the TET NSE-FAST strip shown below. The strip that has 4 test reaction wells, 4 positive control wells and 4 negative control wells is placed in an 7 strip holder that is then inserted into a commercial plate reader that uses the luminescence from the reaction well compared to the positive and negative control wells to measure the amount of active NSE in the sample.
The NSE-FAST test reaction well contents are shown below. They include 2-PG, the substrate that the enzyme NSE takes in and changes to PEP, ADP, Luciferin and two tethered enzyme nanobots with a thousand or more enzymes tethered to a silica nanoparticle with the active side facing outward. The first nanobot has the enzyme PK that used the PEP produced by NSE to change ADP to ATP. The 2nd nanobot is Luciferase that allows fireflies to light up that takes ADP and Luciferin to emit photons.
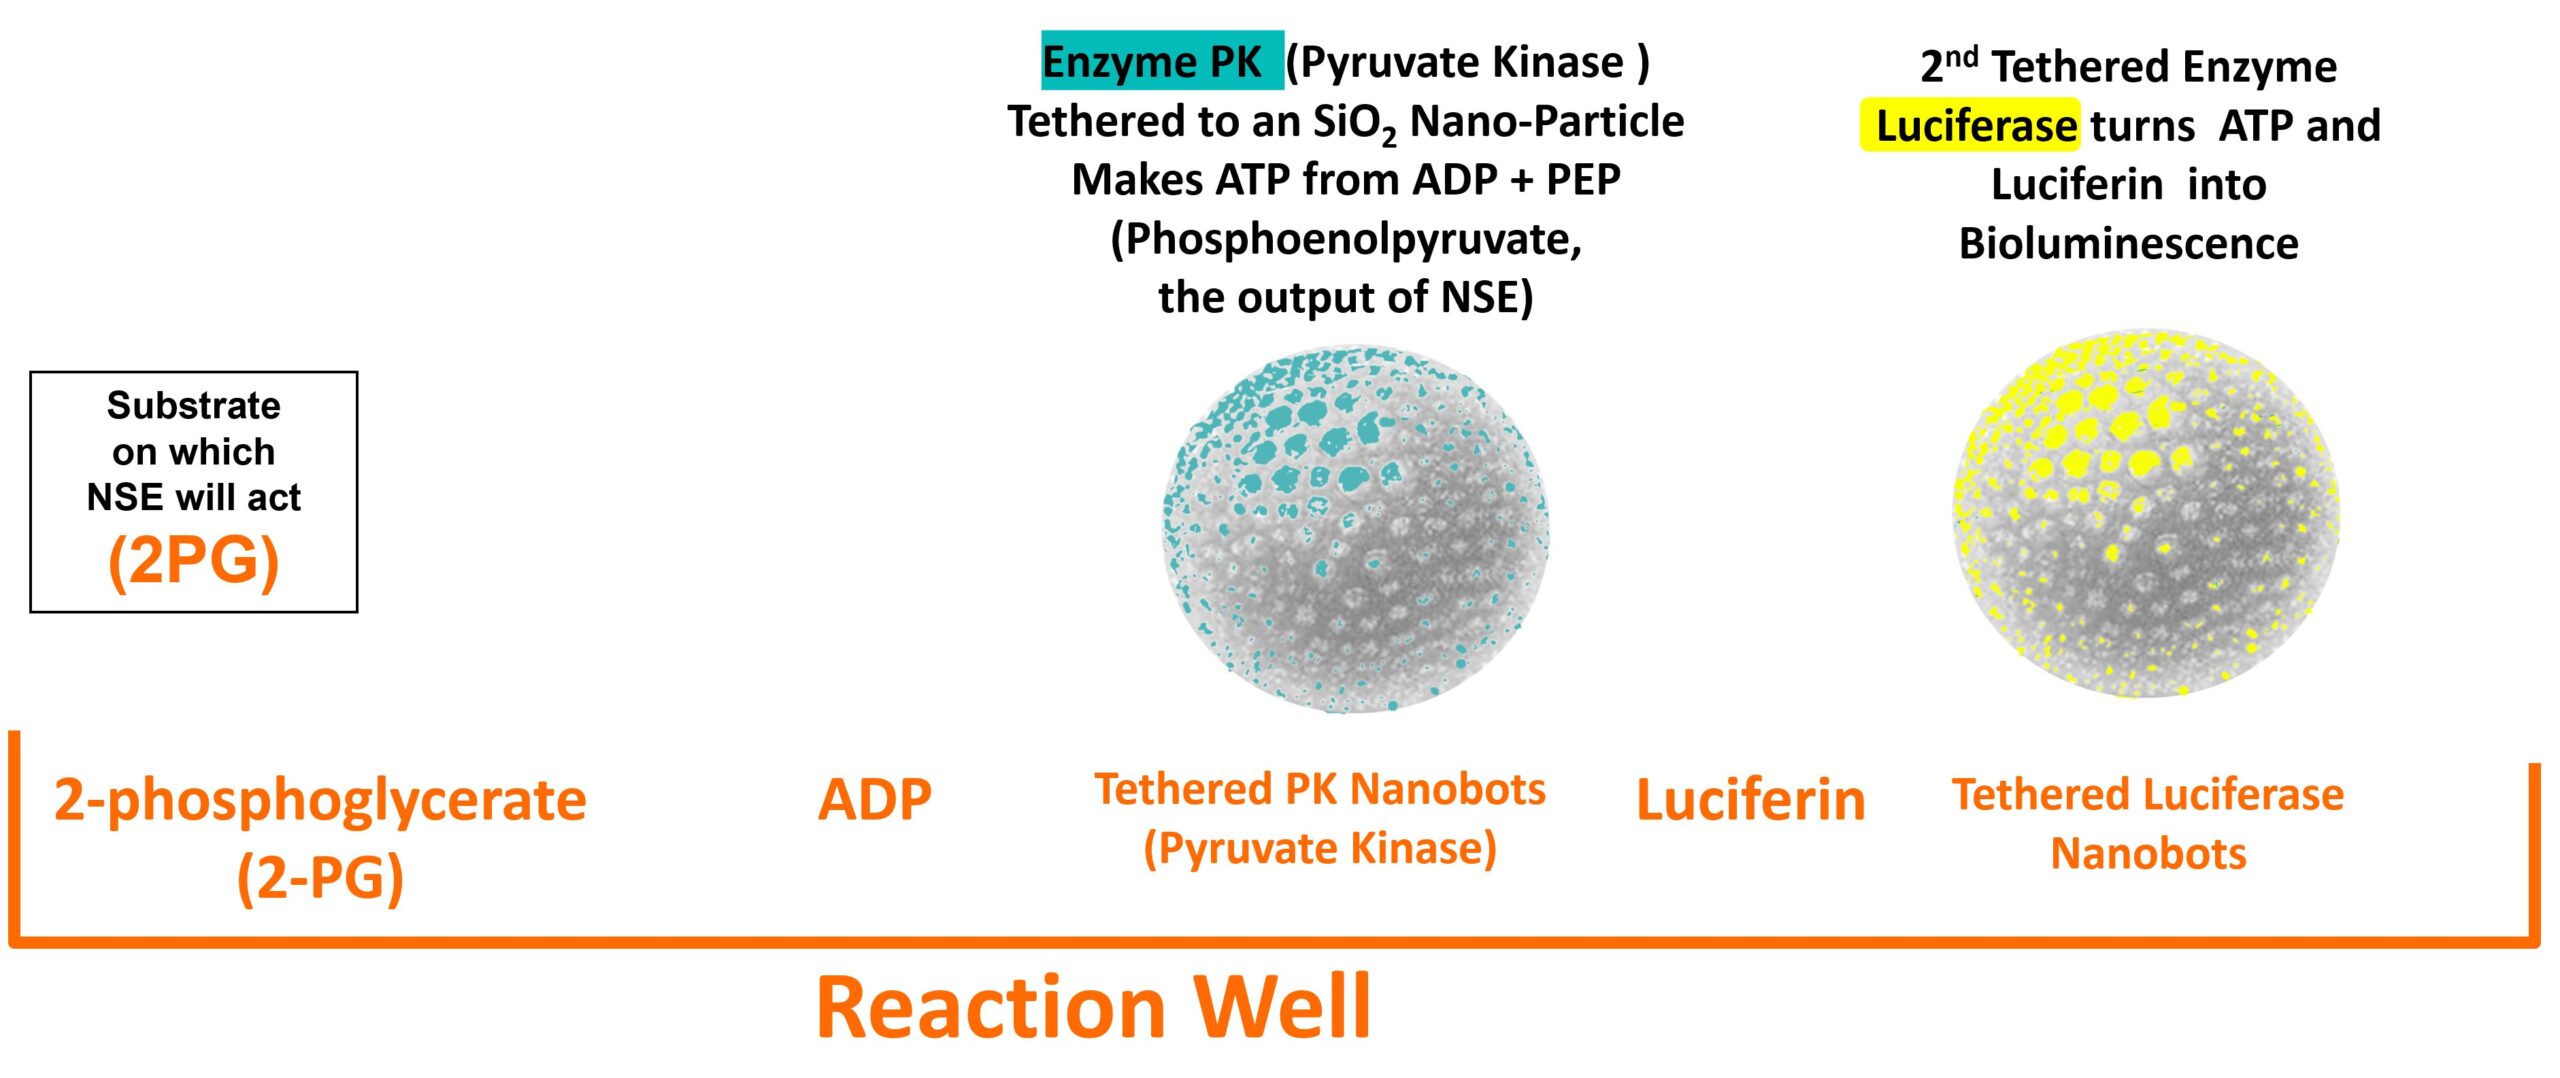
Negative control wells have everything in the reaction well above except for the 2-PG. Positive control wells include a freeze dried specific amount of enolase that will activate when plasma wets the well contents.
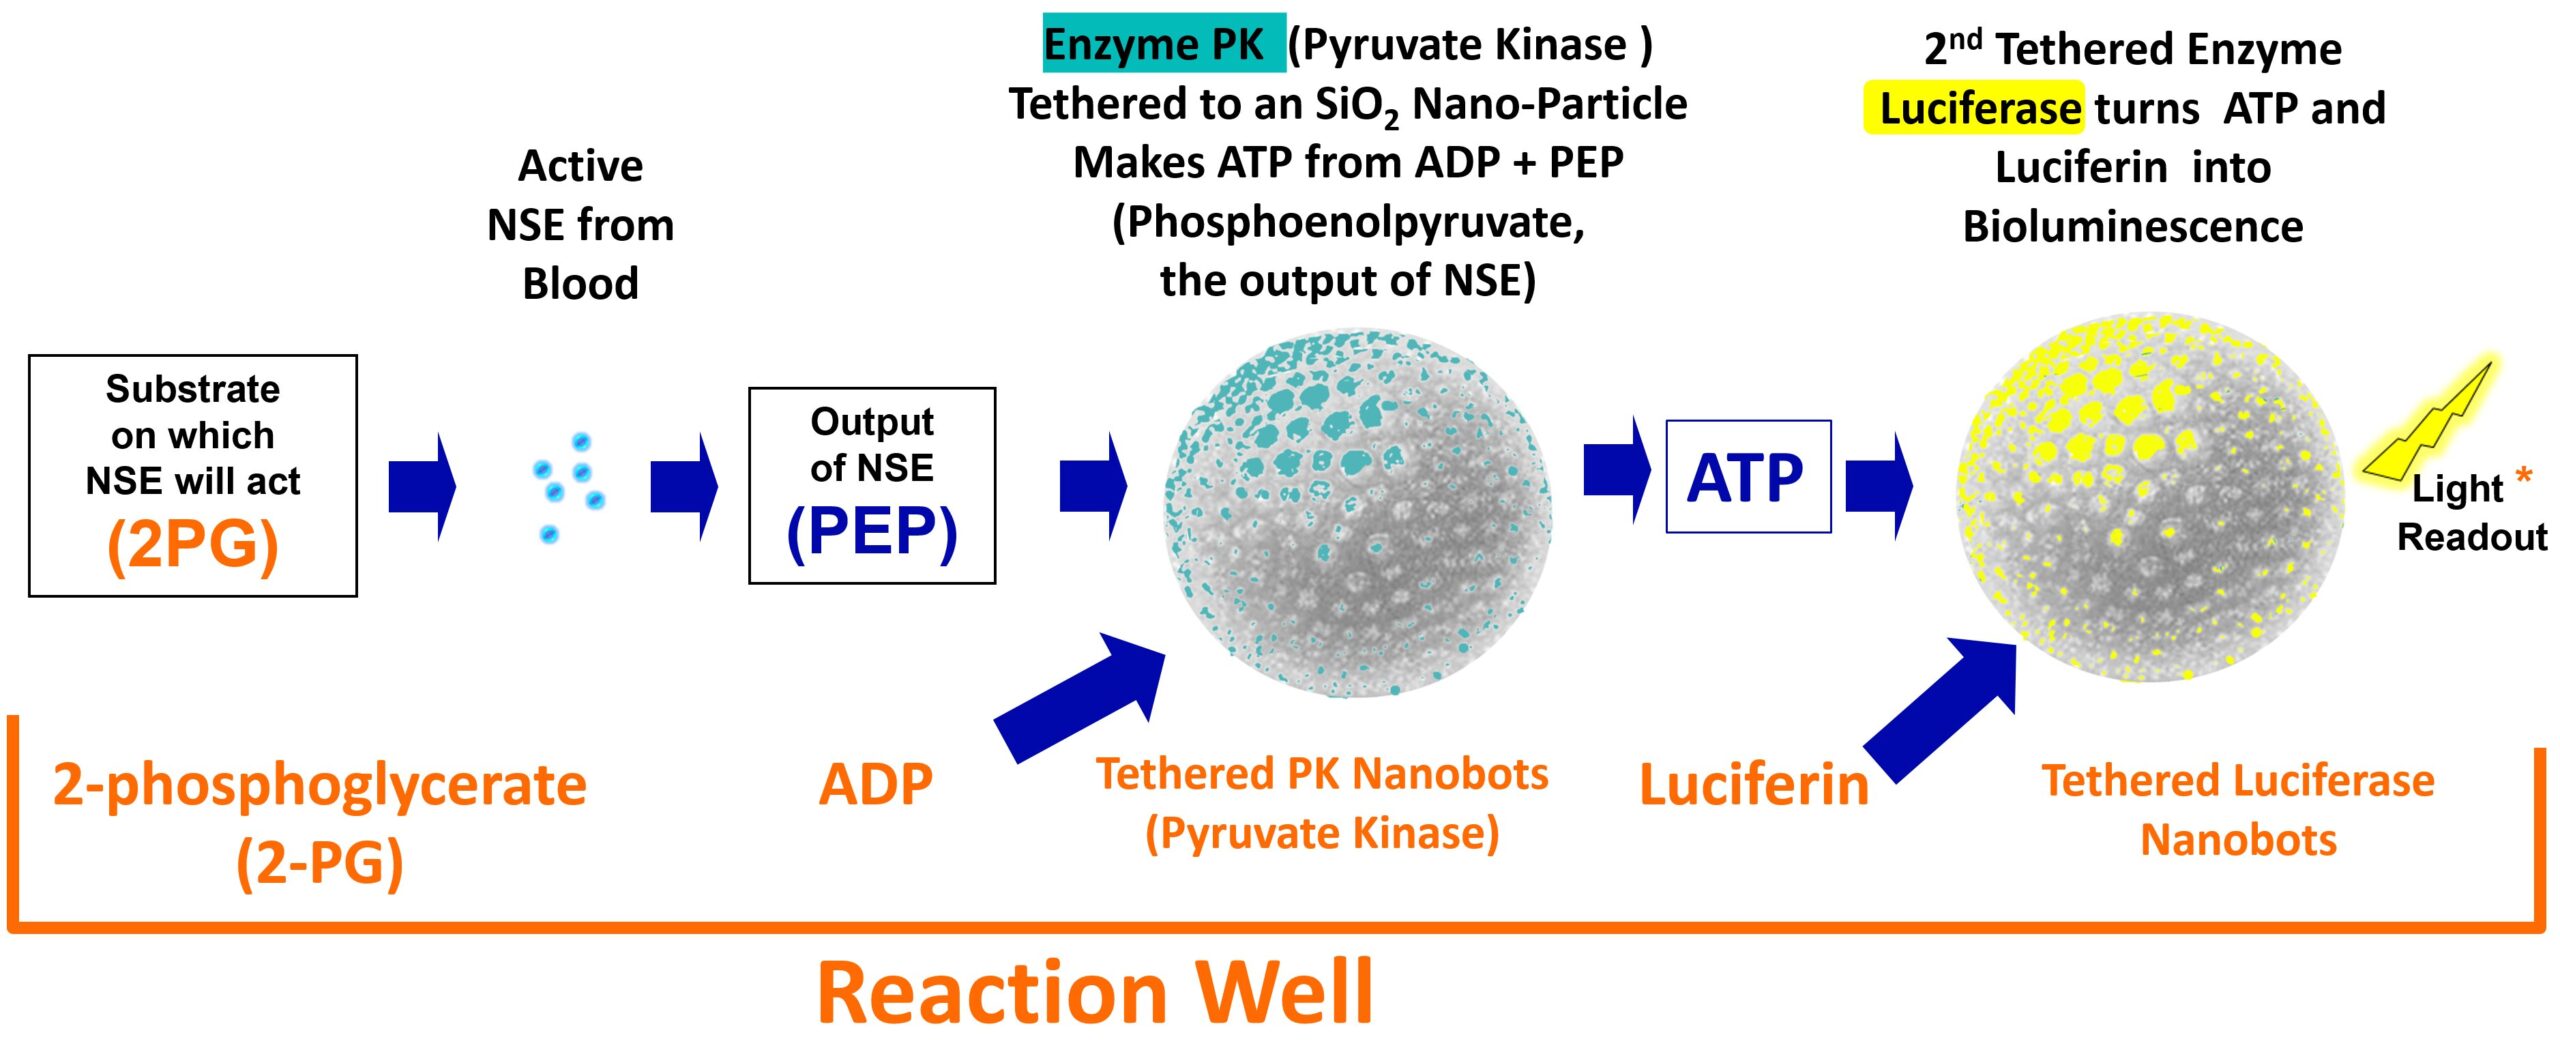
The diagram below shows the steps that occur as the catalytic reaction occurs to create luminescence when there is enzymatically active NSE in the plasma sample placed into the reaction well.
- Active NSE molecules that are in the plasma pipetted into the reaction well hydrate the freeze dried contents and begin converting 2PG to PEP at up to a thousand conversions per second per NSE molecule.
- Once the PEP is available the PK nanobots will begin converting the PEP plus ADP to ATP.
- Once the ATP is available, the luciferase nanobots will begin taking the luciferin and ATP in to emit one photon per ATP molecule
If each enzyme can do up to a thousand conversions per second than a nanobot with a thousand enzymes can do a million per second and with a thousand nanobots you get a billion per second. So with the 2PG, ADP and Luciferen saturated in the wells, the limitation on light output is only the amount of active NSE.
Product In Action
The VIDEO (to the right) shows the speed at which this assay works with first results within 30 seconds of insertion in the plate reader.
Current State Of Testing
The Neuron Specific Enolase Functional Activity Stroke Test (NSE-FAST) has been bench tested, animal tested (see publications) and tested in two human pilot studies. These are a study in patients presenting with stroke symptoms at the Guthrie Stroke Center in Pennsylvania and a test in Mixed Martial Arts (MMA) fighters.
Descriptions of these pilots and the results obtained can be seen in the below links.
*article in publication.
NSE-FAST Market Research
TET Medical was interested in better understanding current diagnostic stroke protocols and refining the target product profile for their lead compound, TET-NSE-FAST. TETmedical hired Biocom Consulting that conducted a total of 7 in-depth telephone interviews with U.S. experts (4 Emergency Department Chairs and 3 Neurologists) between Jan. 27th and Mar. 9th, 2023. Interviews were 1 hour in duration and the physicians were blinded to the company and compound
The Market Research Objectives were:
- Understand current diagnostic stroke protocols and challenges
- Determine current management of stroke cases (risks, diagnostic uncertainty, etc)
- Gauge physician interest in blinded product profile and potential utility within current diagnostic protocols
Conclusions
- KOLs interviewed were enthusiastic about the NSE-FAST product profile
- Consensus that the assay was highly differentiated and would provide greater diagnostic certainty, especially in uncertain cases
- Several recommended more distinct differentiation from prior assays to avoid initial confusion
- There was significant interest in using the assay early, along with CT, in all acute stroke suspected cases
- Sensitivity and specificity of at least 90% would be well received, with even greater confidence at higher levels
- Some KOLs responded favorably to inclusion of clinically relevant data (cases missed without MRI and/or avoidance of tPA) tools provide clinical guidance but have significant limitations
- When CT imaging is negative, physicians rely heavily on degree of disabling symptoms to drive diagnosis and treatment
- Despite diagnostic advances, experts cited numerous clinical scenarios that are diagnostically challenging.
- Experts indicated 3 major areas of unmet need in ischemic stroke: greater diagnostic certainty, improved detection in difficult cases and improved pre-hospital diagnosis.
Preliminary US Stroke Opportunities
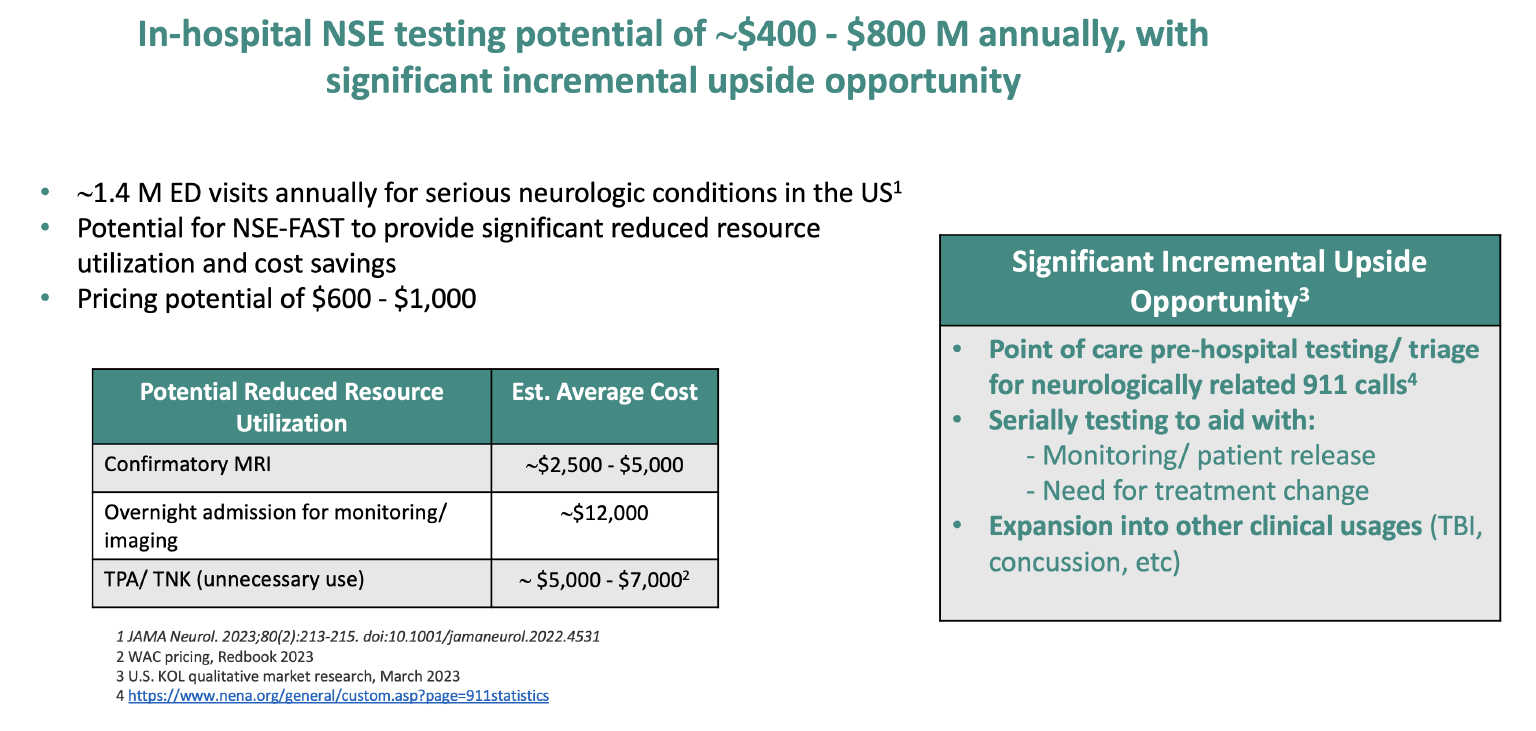
The slide below from the report describes an annual US potential market of between $400M and $800M.
Go to Market Strategy
We do not aim to change the flow and standard of care in stroke, thus assuring fast adoption. Our stroke clinical trial for FDA approval will begin in the second quarter of 2023 with sites at Guthrie Stroke Center in Northern Pennsylvania and Weill Cornell Medicine at the New York Presbyterian Hospital, the top hospital in New York City where our study has already received IRB approval without patient informed consent.
Our first customers will be Emergency Departments. There, all patients admitted with suspicion of stroke receive a CT scan – which if negative, rules out hemorrhage. TET NSE-FAST will then be performed at the same time as the regular IVD blood analysis. If negative, TET NSE-FAST provides tremendous value: to the patient (reduces risk of bleed with TPA); to the payer and hospital system (patients can be discharged, saving over $20k in TPA and admission costs; reduce litigation risk). If positive, TET NSE-A provides additional assurance that recent brain injury has occurred, helping with treatment decisions. We expect the training study in 1-2 center for the TET NSE-FAST IVD assay to begin in the fall of 2023, the pivotal study in 3-10 center to run in 2024 with FDA approval to follow.
Current State of Testing
The Neuron Specific Enolase Functional Activity Stroke Test (NSE-FAST) has been tested in animals (see publications) and in two tests in humans. These include the Guthrie Pilot Study in patients presenting with stroke symptoms and a test in Mixed Martial Arts (MMA) fighters.
Descriptions of the Guthrie Pilot Study and MMA brain injury pilot and the results obtained can be seen in below.
Guthrie Pilot Stroke Study
The TET NSE-FAST provides an objective measure of acute brain injury associated with strokes – the leading cause of disability in the US, but improperly diagnosed in the ambulance half of the time. Today, the gold standard for identifying a stroke is the NIH Stroke Score (NIHSS) based on patient symptoms only.
A pilot study in patients presenting with stroke symptoms was run at the Gutherie Stroke Center in northern Pennsylvania with results pending publication that demonstrated the utility of the NSE-FAST for detecting acute brain injury.
MMA Pilot
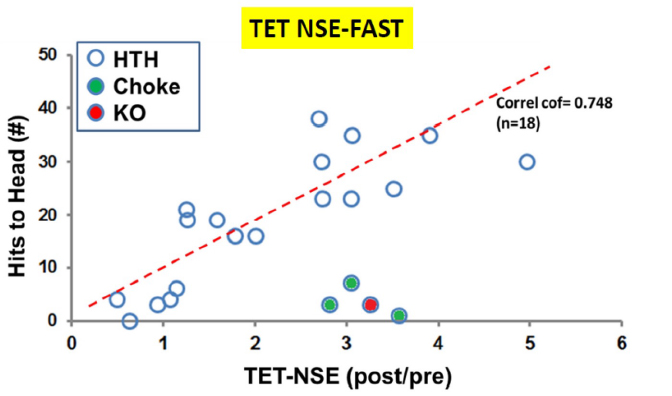
To evaluate applying TET to concussion, the TET assay was brought to a mixed martial arts tournament in Rochester, NY where fighters had blood drawn and measured for NSE activity before and after a 15 minute fight. Students in the audience counted the times each fighter was hit in the head. The plot below shows a number of important aspects of the NSE-FAST.
1. That active NSE can me measured within minutes of the neuronal injury as the 2nd test was run immediately after the 15 minute fight.
2. That the test is quantitative as the more hits to the head the more active NSE is released into the bloodstream
3. The amount of active NSE rises dramatically with levels as high as 5x (400% increase) over the pre-fight level.
4. That the NSE-FAST is able to detect neuronal injury from oxygen deprivation (Ischemia) as the green dots representing chokes to unconsiousness with few hits to the head, were equivalent to 20 to 30 hits.